Why does weight loss get harder the longer you diet?
Your body treats a caloric deficit like a famine. Within weeks, the thyroid axis dials down — active T3 drops while inactive reverse T3 (rT3) rises and blocks thyroid receptors — lowering cellular ATP turnover. The sympathetic nervous system follows, downregulating UCP1 in brown fat so less energy is dissipated as heat. The result: your metabolism slows to defend your current weight. If you are here looking into weight loss injections, the sections below walk through the process from the first quote to the finished job.
How persistent is the metabolic slowdown?
Very. The Biggest Loser 6-year follow-up showed that contestants' metabolisms stayed suppressed years after the competition ended — even after regaining weight. This is why "eat less, move more" fails as a long-term strategy: the body's defenses outlast the diet.
The short version
- The body treats a caloric deficit like a famine: within weeks active T3 drops while inactive reverse T3 rises and blocks thyroid receptors, lowering cellular ATP turnover.
- The sympathetic nervous system then downregulates UCP1 in brown fat, so less energy is dissipated as heat and metabolism slows to defend the current weight.
- The Biggest Loser 6-year follow-up showed contestants' metabolisms stayed suppressed years after the competition ended, even after they regained weight.
- GLP-1 therapies blunt the starvation-response hormones leptin, ghrelin, and PYY that drive rebound hunger when calories stay restricted for weeks.
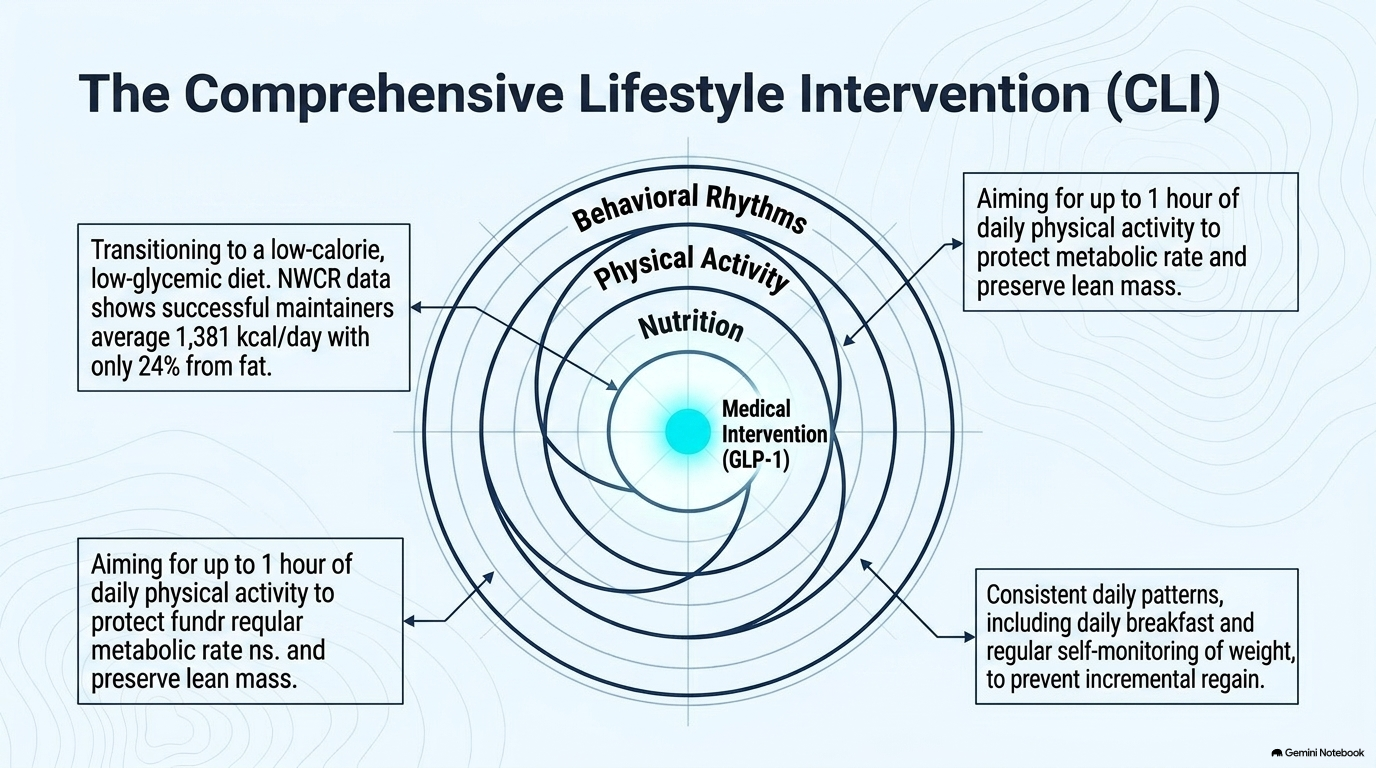
- Pairing medication with a comprehensive lifestyle intervention protects muscle and metabolic rate, which the article calls a clinical requirement rather than an option.
- Most patients see meaningful changes by week 4-8 as appetite regulation stabilizes, and the 3-4 month evaluation decides whether to continue, adjust dosage, or switch medication.
What actually breaks the cycle?
Physician-supervised programs that combine GLP-1 medication with a structured lifestyle plan. GLP-1 therapies blunt the starvation-response hormones (leptin, ghrelin, PYY) that drive rebound hunger, while a comprehensive lifestyle intervention protects muscle and metabolic rate during the deficit. In Abilene, weight management programs pair medication with this structured approach — a clinical requirement, not an option.
What should you expect in the first 12 weeks?
Most patients see meaningful changes by week 4-8 as appetite regulation stabilizes. The clinical standard is a 3-4 month evaluation: if weight loss is adequate and side effects are manageable, you continue; if not, dosage adjusts or the medication is switched. Sustainable loss — not crash loss — is the goal.